White House trying to sabotage 2020 election

The White House is trying on several fronts to prevent people from voting and to undermine the legitimacy of the vote on November 3. It seems that the president has come to the realization that the only way he can win is by cheating.
There is more and more polling evidence that Joe Biden holds a commanding lead in the election with only three months to go. Even swing states show consistent margins in Biden’s favor. There is going to be an “October surprise” of course, but people are unlikely to believe anything coming out of the administration that seeks to denigrate Biden at this late date.
On the other hand, there is Michael Cohen (the president’s former lawyer) who was sentenced to jail for the bribe paid to a woman to keep her quiet about having adulterous intercourse with Him until after the 2016 election… Mr. Cohen plans to have yet another book about the president’s racist and anti-Semitic remarks in private, among other nasty tidbits, out in October as well.
There is also John Brennan, former CIA director, whose memoir will be out in October too. He writes that the president had no interest in learning the truth about Russia’s interference in the 2016 election. Presumably, the president is expecting help with the 2020 election also.
Lies about the election
First, there are the statements that have come thick and fast recently claiming that the vote will be “rigged” and that mail-in voting is “fraudulent”– when all evidence is to the contrary. He has also stated that the election won’t be called within a reasonable time because of mail-in ballots (which may be true from his point of view since he has such a short attention span.)
Voting restrictions
Second, there are the attempts by several states to restrict voting times, places, and absentee qualifications. These have been going on for many years. Voting restrictions were worse during the years after Reconstruction, when white supremacists were able to prevent anyone who did not meet their standards of whiteness from voting.
Many restrictions have made a comeback since the Supreme Court invalidated a critical portion of the Voting Rights Act that prevented states with a history of discrimination from unilaterally passing new restrictions.
Not supporting state election offices
Third, there is the inadequacy of the federal monetary and strategic support for state’s efforts to make voting safer. Pandemic relief bills that include money to help state election offices have stalled in Congress.
Damaging the USPS
Fourth, there is a concerted attack on the ability of the US Postal Service (USPS) to deliver mail. The USPS will be required to handle an unprecedented volume of mailed ballots in November.
The administration has installed a new postmaster for USPS who has engaged in a sudden crackdown on the methods mail carriers have been using to ensure timely delivery. He claims that the new policies are meant to save money, but they are not needed because for the first time in years, USPS is not under immediate threat of running out of money.
Concerns that the pandemic would lead to USPS insolvency were alleviated when an increase in package deliveries (on which USPS makes a profit) salvaged the bottom line. As a result, they were able to refuse a loan offered by the administration which carried onerous terms.
Then the new Postmaster General sent out a memo “urging postal staff to leave behind mail at distribution centers if they thought it would cause a delay for letter carriers. Another memo stated that the USPS would be looking to cut transportation and overtime costs…” Yet another memo signaled a new program that planned to ” send letter carriers out to deliver mail more quickly in the morning by prohibiting them from sorting any mail in their offices before they go.” (The Intercept, July 29)
The bottom line is that the president wants to privatize USPS and has installed an outsider as Postmaster General who intends to make it more “efficient” by prohibiting overtime, reducing multiple drive-outs to deliver mail, and other changes that will only save a little money but slow down delivery of both mail and packages.
USPS is competing with FedEx and UPS for packages, but it is a government agency with a mandate to deliver mail. Although mail is a smaller and smaller component of its service, it is critical for government purposes like balloting, Medicare and Medicaid information, and many other documents.
Feuding with Jeff Bezos
In April, the president called USPS “a joke” (which it certainly wouldn’t agree with) and demanded that they quadruple their package-delivery fees. Apparently he wants this because USPS is used by Amazon to deliver many of its packages, and he has a running feud going on with Jeff Bezos, who is Amazon CEO and also owns The Washington Post (although he exercises no editorial control over it.) See this article about USPS changes in the Post July 14.
The Post, of course, is a newspaper that regularly prints unflattering articles about the administration, and is, as he claims, “fake news” and “the enemy of the people.” In fact, most newspapers, including the Post, rigorously fact-check everything they print and immediately retract anything shown to be wrong. As to the latter, it would seem that the president is the one who is the people’s enemy.
Ironically, if USPS were to dramatically increase their package fees, Amazon would abandon it (building out their own delivery service instead), and USPS would suffer financially as a result– a self-defeating proposition. Don’t expect the president to understand things like “essential government services” or the role that USPS serves in delivering packages to out-of-the-way places that FedEx and UPS don’t want to serve.
Georgia youth summer camp had major outbreak of COVID-19 with 76% of testees positive: MMWR

The Morbidity and Mortality Weekly Report (MMWR) for July 31 had this: A summer camp attended by children and teenagers aged 6-19 was affected by an outbreak of COVID-19. There was an overall “attack rate” of 44% (260 of 597) but only 58% were tested… 76% (260/344) of those tested had positive results for SARS-COV-2 antigens. 27 attendees were excluded from analysis because they were from out of state.
The camp was in Georgia, and was said to have required a negative test within 12 days before attendance. Staff members (120 people aged 14-59) were required to wear masks but the attendees were not. The session began with training held June 17-20, followed by camp starting June 21 and scheduled to end on June 27. On June 23, a staff member developed symptoms (chills) and left; the positive test was reported the next day and the camp was emptied out. The Georgia Department of Health began an investigation on June 25.
Here is a quote from the MMWR report:
A total of 597 Georgia residents attended camp A. Median camper age was 12 years (range = 6–19 years), and 53% (182 of 346) were female. The median age of staff members and trainees was 17 years (range = 14–59 years), and 59% (148 of 251) were female. Test results were available for 344 (58%) attendees; among these, 260 (76%) were positive. The overall attack rate was 44% (260 of 597), 51% among those aged 6–10 years, 44% among those aged 11–17 years, and 33% among those aged 18–21 years (Table). Attack rates increased with increasing length of time spent at the camp, with staff members having the highest attack rate (56%). During June 21–27, occupancy of the 31 cabins averaged 15 persons per cabin (range = 1–26); median cabin attack rate was 50% (range = 22%–70%) among 28 cabins that had one or more cases. Among 136 cases with available symptom data, 36 (26%) patients reported no symptoms; among 100 (74%) who reported symptoms, those most commonly reported were subjective or documented fever (65%), headache (61%), and sore throat (46%).
Szablewski CM, Chang KT, Brown MM, et al. SARS-CoV-2 Transmission and Infection Among Attendees of an Overnight Camp — Georgia, June 2020. MMWR Morb Mortal Wkly Rep. ePub: 31 July 2020. DOI: http://dx.doi.org/10.15585/mmwr.mm6931e1
This summer camp, apparently a typical one, lasted only two days out of a planned seven, after a staff member developed symptoms and was sent home. It was too late by then to prevent 76% of those tested from developing COVID-19 in the two weeks after they went home.
The only unusual feature of this outbreak was that 74% of the positive cases had symptoms– mostly fever, headache, and sore throat. Note that the “attack rate” was highest among the youngest attendees.
What can I say that hasn’t already been said? Maybe wearing masks would have helped? Maybe group sing-alongs and cheering was a bad idea?
It is possible, indeed likely, that the first patient with symptoms was infected just prior to arrival at the camp, since it appears from the timeline that they arrived June 17 and symptoms started June 23. Having a negative test up to 12 days before arrival would not have been sufficient to prevent this occurrence.
I’m writing this post today for two reasons: first, I don’t know what is going on with these organized religions today. Two, I wrote several posts about the origins of both religions in the eras surrounding the birth of the Buddha and the origins of the Vedas (documents that form some of the foundations of Hinduism.)
The Hindu religion is closely associated with India, home to the second-largest population in the world today (roughly 1.353 billion people in 2018 and growing about 1% a year or 13.53 million– meaning there are roughly 1,380,060,000 people there today. Actually, Worldometer estimates that there are 1,380004,385 people in India on July 31, 2021.)
According to Wikipedia, India is nearly 80% Hindu, and Nepal is 81%. Bali is also 84% Hindu. Wikipedia lists these other countries with large Hindu populations: Bangladesh (14 million or 8.5%), Indonesia, Pakistan (3.6 million or 1.8%), Sri Lanka (2.7 million or 12%), Malaysia, Singapore, United States, Myanmar, United Kingdom, Canada, South Africa, Mauritius, and the Caribbean or West Indies.
Buddhism is associated with China, but not quite as strongly as Hinduism is with India. China has the largest population, estimated at 1,439,323,776 today by Worldometer. Some say that India’s population will overtake that of China soon.
China has been home to Buddhism since Chinese pilgrims (some of them Taoist monks) visited India in the early years of the common era.
Time.com says, “Official [Chinese government] statistics don’t exist, but the Pew Research Center, which surveys religious belief worldwide, estimates some 245 million Buddhists in China, around 18% of the total national population.”
According to the Council on Foreign Relations, “The state [the People’s Republic of China, herein called the Chinese government] recognizes five religions: Buddhism, Catholicism, Daoism, Islam, and Protestantism. The practice of any other faith is formally prohibited, although often tolerated, especially in the case of traditional Chinese beliefs.”
Several smaller countries have significant populations of Buddhists. Taiwan, which aspires to be a separate country from mainland China but has some difficulty with international recognition, has some eight million Buddhists. Most of them are adherents of the Mahayana (“Greater Vehicle”) sect.
Other countries with large Buddhist populations: Tibet (legally part of China), Japan (45 millions), Thailand (64 million or 93% of the country), Sri Lanka (14 million or 69%), Nepal (3 million or 10%), Myanmar/Burma ( 38 million or 80%), Mongolia (1.5 million or 55%), Malaysia (5 million or 20%), Laos (4 million/ 66%), South Korea (11 million/ 23%), Cambodia (13.7 million / 97%), and Bhutan (0.5 million/ 75%). For the world, the total of Buddhists is 487 million or 7.1%. All this is from Wikipedia.
According to Wikipedia, “… an IndiaSpend analysis of 2011 Census data … there are more than 8.4 million Buddhists in India and 87% of them are neo-Buddhists or Navayana Buddhists. They are converted from other religions, mostly Dalits (Scheduled Caste) who changed religion to escape Hindu caste oppression.” (This means about 0.8% of India is Buddhist.)
That suggests another topic, the origins of the caste system, about which I have some thoughts and some need to research in order to form opinions. Not now.
Both religions started in Northern India.
As I noted in previous posts, Buddhism in India may be considered to have begun as an outgrowth of Hinduism– when the Buddha rejected the teachings of two sramana experts on meditation. There are many aspects of Hinduism which the Buddha found objectionable.
I won’t get into that now, but there were reports of Buddhists in China before 300 BCE. The Han emperor Ming Ti (reigned CE 57-75) is said to have had a dream that was interpreted to him as a vision of the Buddha.
In reality, it was more of a gradual process both before and after the emperor’s dream. The Silk Road trade route was a major factor in the wide spread of Chinese Buddhism, especially after the first century of the common era– the Han dynasty (206 BCE-220 CE.)
Buddhist tantras or magical invocations (mantras) were popular because of their resemblance to Taoist practices. This made Vajrayana, or Tibetan Buddhism, particularly engaging for Chinese Taoists.
Not a good place to stop.
This is not a good place to stop but sometimes you have to stop for extraneous reasons and that is the case now. So I promise more later, especially if i get some “likes”… even if I don’t get any likes or comments. No, I don’t care if you like it or not, but it’s always nice to be liked. Really, I have to stop now. Don’t stop now. Stop now. Don’t stop now. Don’t. Stop. Now.
[microphone falls to floor]

This study came out on JAMANETWORK July 30, and it is devastating for the accepted notion that children do not pose a COVID-19 risk to adults. The study shows high levels of SARS-COV-2 antigen in swabs from the noses of small children presenting with symptoms or exposure to the virus. Children under five have more virus, and children 5-17 have the same amount of virus as adults.
It is worth quoting extensively; here is an excerpt from Methods:
This cohort included all individuals aged younger than 1 month to 65 years who tested positive for SARS-CoV-2. Patients with symptoms suggestive of a COVID-19–compatible illness and/or high-risk exposures were tested. We included the first sample tested for patients with multiple samples. Because patients with severe infection have lower CT values [reference 4] we excluded 7 children who required supplemental oxygen support. We also excluded 7 asymptomatic patients, 29 patients with unknown duration of symptoms, and 19 patients whose symptoms started more than 1 week prior to testing.
https://jamanetwork.com/journals/jamapediatrics/fullarticle/2768952
Here is an excerpt from the results section:
Our final cohort included 145 patients with mild to moderate illness within 1 week of symptom onset. We compared 3 groups: young children younger than 5 years (n = 46), older children aged 5 to 17 years (n = 51), and adults aged 18 to 65 years (n = 48). We found similar median (interquartile range) CT values for older children (11.1 [6.3-15.7]) and adults (11.0 [6.9-17.5]). However, young children had significantly lower median (interquartile range) CT values (6.5 [4.8-12.0]), indicating that young children have equivalent or more viral nucleic acid in their upper respiratory tract compared with older children and adults (Figure). The observed differences in median CT values between young children and adults approximate a 10-fold to 100-fold greater amount of SARS-CoV-2 in the upper respiratory tract of young children.
https://jamanetwork.com/journals/jamapediatrics/fullarticle/2768952
In other words, in 46 children under 5 compared to 48 adults (18-65 y/o), samples taken from the nasopharynx (back of the nose) showed higher median virus levels and children aged 5-17 had similar virus levels (CT means amplification cycle thresholds, the inverse of virus numbers; lower CT means more virus, or: “lower values indicating higher amounts of viral nucleic acid.”)
In fact, “younger children had significantly lower median CT values” and this means “approximate[ly] a 10-fold to 100-fold greater amount of SARS-CoV-2 in the upper respiratory tract of young children.”
So younger children had roughly 10-100 times as much virus as adults in their noses, on average. The report concludes:
Thus, young children can potentially be important drivers of SARS-CoV-2 spread in the general population, as has been demonstrated with respiratory syncytial virus, where children with high viral loads are more likely to transmit.6 Behavioral habits of young children and close quarters in school and day care settings raise concern for SARS-CoV-2 amplification in this population as public health restrictions are eased. In addition to public health implications, this population will be important for targeting immunization efforts as SARS-CoV-2 vaccines become available.
https://jamanetwork.com/journals/jamapediatrics/fullarticle/2768952
This result contrasts with previous studies that supposedly showed less transmission to and from children. This report was actually “accepted for publication on May 31”– a two month delay in some very important news. There is a contradiction here that needs to be examined closer.
Previous research on children:
Let us look at the studies that supposedly showed less transmission in children.
This review, titled “Children are unlikely to be the main drivers of the COVID‐19 pandemic – A systematic review” from Acta Pediatrica dated May 19, asserts that “Data on viral loads were scarce, but indicated that children may have lower levels than adults, partly because they often have fewer symptoms, and this should decrease the transmission risk.”
Whatever else it says, this review is already obsolete– and the data it is missing (viral loads) was “accepted for publication” nine days before this one was published.
Another review, titled “Role of children in the transmission of the COVID-19 pandemic: a rapid scoping review” from BMJ (British Medical Journal) Open, says it was “received May 1” but also says it included studies “from 1 December 2019 until 28 May 2020. ” It states that, of 14 (1099 were considered) studies finally included, these statistics were found:
Although no complete data were available, between 15% and 55%–60% were asymptomatic, and 75%–100% of cases were from family transmission. Studies analysing school transmission showed children as not a driver of transmission.
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7311007/
Children are not transmitters to a greater extent than adults. There is a need to improve the validity of epidemiological surveillance to solve current uncertainties, and to take into account social determinants and child health inequalities during and after the current pandemic. … There is also insufficient information on the child population as a source of transmission of the infection. Despite this, in the majority of countries, one of the first measures adopted has been the closure of schools…
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7311007/
One reason schools were closed is that influenza is known to be widely spread through schools to adults. While the novel coronavirus is not thought to be as contagious as influenza, it seemed a wise precaution at the time. Now the pressure to reopen schools seems to be ignoring that wisdom.
Since schools have been closed, there is little surprise in studies finding that most infected children got the virus from adults in their households.
Next, we have a report titled “COVID-19 in children: the link in the transmission chain” and published online March 25 in Lancet Infectious Diseases. (This is actually an analysis of a study written up by Chinese doctors; the original is available here.) It includes 36 children (1-16 y/o), about half of whom had pneumonia on CT scan but all of whom had clinically mild disease. It concludes thusly:
The most important finding to come from the present analysis is the clear evidence that children are susceptible to SARS-CoV-2 infection, but frequently do not have notable disease, raising the possibility that children could be facilitators of viral transmission. If children are important in viral transmission and amplification, social and public health policies (eg, avoiding interaction with elderly people) could be established to slow transmission and protect vulnerable populations. There is an urgent need to for further investigation of the role children have in the chain of transmission.
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7156154/?report=reader
This would suggest caution in light of the possibility that children could transmit infection without appearing to be sick.
Then there is this Medscape article from July 10, titled “Children Rarely Transmit SARS-COV-2 Within Households”… It quotes a Swiss study that collected all patients identified by Geneva University Hospital surveillance between March 10 and April 10. Of 4310 patients with COVID-19, only 40 were under 16. The mild illnesses of these children is shown in this quote from the Results:
29 (74%) patients were previously healthy; the most frequently reported comorbidities were asthma (10%), diabetes (8%), obesity (5%), premature birth (5%), and hypertension (3%). Seven patients (18%) were hospitalized to the ward, for a median duration of 3 days (IQR: 2–4); reasons for admission were surveillance for nonhypoxemic viral pneumonia (n = 2), fever without source (n = 2), apparent life-threatening event (n = 1), and sepsis-like event (n = 1); 1 paucisymptomatic child admitted because both parents had severe COVID-19 (n = 1). No patient required ICU admission or SARS-CoV-2–specific therapies. The others 32 patients were managed as outpatients. All patients had a complete resolution of symptoms by day 7 after diagnosis.
https://pediatrics.aappublications.org/content/146/2/e20201576
The familial clustering of cases was apparent from this data, headed Familial Clusters:
Familial cluster evaluation revealed a t number of 4 household members per family (IQR: 3–4). Among the 111 HHCs of study children, mothers predominated (n = 39), followed by fathers (n = 32), pediatric siblings (n = 23), adult siblings (n = 8), and grandparents (n = 7) (Fig 1). Adult HHCs were suspected or confirmed with COVID-19 before the study child in 79% (31/39) of cases. In only 8% (3/39) of households did the study child develop symptoms before any other HHC (Fig 1). Interestingly, 85% (75/88) of adult HHCs developed symptoms at some point, compared with 43% (10/23) of pediatric HHCs (P < .001). Also, 92% (36/39) of mothers developed symptoms, compared with 75% (24/32) of fathers (P = .04).
https://pediatrics.aappublications.org/content/146/2/e20201576
Note that it appears that 79% of child cases appeared to be preceded by, probably brought on by, adult cases. From the Discussion section:
In 79% of households, ≥1 adult family member was suspected or confirmed for COVID-19 before symptom onset in the study child, confirming that children are infected mainly inside familial clusters.6 Surprisingly, in 33% of households, symptomatic HHCs tested negative despite belonging to a familial cluster with confirmed SARS-CoV-2 cases, suggesting an underreporting of cases. In only 8% of households did a child develop symptoms before any other HHC, which is in line with previous data in which it is shown that children are index cases in <10% of SARS-CoV-2 familial clusters10; however, with our study design, we cannot confirm that child-to-adult transmission occurred.
https://pediatrics.aappublications.org/content/146/2/e20201576
This study does NOT show that children don’t transmit infections to adults. It shows that most children detected with infection caught it from adult family members. As the authors noted at the end:
This study has some limitations. The study sample likely does not represent the total number of pediatric SARS-CoV-2 cases during this time period. Indeed, patients with milder or atypical presentation might not have sought medical attention. Moreover, the recall of symptom onset among HHCs might be inaccurate, although this seems for once less likely because of the confinement measures and anxiety in the community.
https://pediatrics.aappublications.org/content/146/2/e20201576
An editorial in the same issue of Pediatrics quotes a Chinese study, which is well worth quoting again. From its Results section:
RESULTS: A total of 74 pediatric patients with COVID-19 were included in this study. Of the 68 case patients whose epidemiological data were complete, 65 (65 of 68; 95.59%) were household contacts of adults. Cough (32.43%) and fever (27.03%) were the predominant symptoms of 44 (59.46%) symptomatic patients at onset of the illness. Abnormalities in leukocyte count were found in 23 (31.08%) children, and 10 (13.51%) children presented with abnormal lymphocyte count. Of the 34 (45.95%) patients who had nucleic acid testing results for common respiratory pathogens, 19 (51.35%) showed coinfection with other pathogens other than SARS-CoV-2. Ten (13.51%) children had real-time reverse transcription polymerase chain reaction analysis for fecal specimens, and 8 of them showed prolonged existence of SARS-CoV-2 RNA.
https://pediatrics.aappublications.org/content/146/1/e20200961
Again, most (over 95%) of the 74 patients in this study got their virus from adults in their households.
Another fascinating finding was that 34 children were checked for other pathogens and about half of them showed “coinfection”– meaning that they also had another virus besides SARS-COV-2 in their systems. We’ll see coinfection again in a ski chalet, below.
Also, 13% of the children had the new virus in their stools and most of them had “prolonged” presence of virus in the stool. Fecal-oral transmission of SARS-COV-2 has not been studied and is unlikely in sanitary countries; this route is more likely to be important in places like India and Mexico where sanitary precautions are not universal.
The Medscape article mentions a letter about contact tracing. A French chalet where an English case infected 75% (12 of 15) of his chalet-mates includes a single pediatric case (who had a triple infection):
One pediatric case, with picornavirus and influenza A coinfection, visited 3 different schools while symptomatic. …
All [chalet] cases were negative for other viruses except for the pediatric case, who had a SARS-CoV-2 + picornavirus (rhinovirus or enterovirus) + influenza A(H1N1)pdm09 coinfection. His 2 siblings were negative for SARS-CoV-2, but had an influenza A(H1N1)pdm09 infection and an influenza A(H1N1)pdm09 + picornavirus coinfection, respectively. … At school C, 30% (3/10) of contacts of the pediatric case had a picornavirus infection. … In addition, “classical” human coronaviruses such as HUK1 and NL63 were detected in 16% of contacts without any cross-reactivity with SARS-CoV-2 molecular diagnostics. … the infected child, despite interactions with a large number of contacts in different schools, did not transmit the disease, as evidenced by the large number of negative results of his tested contacts. … It is also possible that the very low viral load of the pediatric case and the subsequent lack of transmission might be related to his coinfection and the co-circulation of respiratory viruses. Viral load was only tested 8 days after his onset of symptoms. The child continued his normal activities and interactions as his symptoms were mild.
https://academic.oup.com/cid/article/71/15/825/5819060
We could go on, but I’m out of time.
Cutting off debate due to time
That’s enough. There is a lack of information on the important question: will opening schools for in-person attendance during an uncontrolled outbreak of a novel disease cause more people to get sick?
There is a reason to think that the answer is yes: what we already know about influenza. When schools are closed, influenza morbidity and mortality goes down.
There is no data on the novel coronavirus that would contradict this observation. There is only unfounded optimism, based on the unusual behavior of this pathogen, which seems to cause less serious clinical manifestations in younger patients.
The new study mentioned at the head of this post shows that, despite mild or inapparent disease, children have equal or greater amounts of virus to spread when they are infected. This turns unfounded optimism into blind “polyanna-ism.”
I suggest keeping schools closed except for children with no internet access and to pick up the meals usually handed out to poor children. Teachers and staff can be first in line, with bus drivers and other essential personnel like health care workers, when a vaccine becomes available in January (I just picked that date because I’m a semi-founded optimist.) Then we can re-open schools in February, after the vaccine has time to take effect.
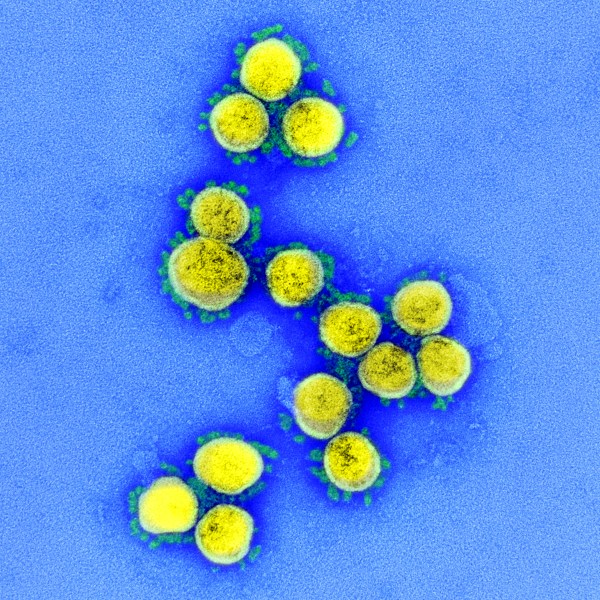
This patient, who had mild symptoms of body aches and sore throat without fever in March and was not tested, presented on April 23 to donate blood and was found to have both antibodies to SARS-COV-2 and viremia on a very sensitive antigen test. He had no antigen on a nasopharyngeal swab test taken after the viremia was found.
The case was reported in the Annals of Internal Medicine on July 17. The finding is particularly puzzling because viremia is unusual in previously published reports of acute cases. Only a minority of acutely ill patients were found to have virus in their bloodstreams.
The case report’s discussion states that the finding was unlikely to be a false positive because they found positive results for two different parts of the virus at low levels. The patient was unlikely to be infectious because of the low levels found; however, the blood bank has decided to lengthen its deferral period from 28 to 56 days after resolution of symptoms.
This is just another puzzling finding to add to all the other odd things that we have learned about this virus. I don’t have any explanations or even speculation to add.

The Union health ministry said in a statement that 21,387 samples were collected in accordance with laboratory standards and were tested between June 27 and July 10 to determine the extent of the spread of the coronavirus disease in Delhi.
“Nearly six months into the epidemic, only 23.48% of the people are affected in Delhi, which has several pockets of dense population,” the Union health ministry, which commissioned the study, said in a statement.
https://www.hindustantimes.com/delhi-news/over-23-of-delhi-s-population-affected-by-covid-19-shows-serosurvey-results/story-Sq1XXdPkfmDdggyNwGdlSK.html
As on July 28, Mumbai has recorded 1,10,846 [sic] COVID-19 cases and 6,184 deaths.
A sero-surveillance study done in Mumbai has revealed that 57% of slum population and 16 per cent of non-slum residents in three civic wards had developed antibodies, indicating many people would already be affected by COVID-19 than the official tally suggests.
The Serological Surveillance for SARS-CoV2 infection was jointly commissioned by NITI Aayog, the BMC and the Tata Institute of Fundamental Research (TIFR).
The sero-surveillance started on June 3 and 6,936 samples out of an estimated 8,870 were collected from slum and non-slum population of three civic wards — R-North, M-West and F-North — in the first half of July.
https://www.thehindu.com/news/national/coronavirus-57-of-mumbai-slum-population-has-developed-antibodies-study/article32216939.ece
As of today, India has had 1,582,028 confirmed cases and 34,956 deaths, with 1,019,740 people recovered from the virus.
These reports are taken from Indian newspaper websites and published July 29. According to Wikipedia, the average age is 29 in India and more than 50% of the population is under 25. This is the youngest average for all countries in the world, according to this 2017 article in Financial Express of India.
For comparison, the median age is 38.2 in the US as of 2018; Maine has the highest median at 45 and Utah the lowest at 31.
The penetration of coronavirus is intense in the slums of Mumbai, yet the youth of the population seems to have reduced morbidity and mortality. Testing rates have been very low, although no exact data is available, only totals for the country. Authorities are freely admitting that funds for testing and treatment are simply not available in the needed amounts.
This article in the Washington Post on July 17 argues that India’s low death rate is due to under-reporting. The article also states that the pandemic is spreading unchecked throughout the country.
The hospital situation in India is surely as bad as that in Mexico. Fortunately for those who wish to know, there is better reporting about what is going on there. I was unable to locate any seroprevalence studies for Mexico at all.
Another statistic, not quite relevant but of interest: life expectancy at birth in India in 2020 for men is 68.4 and for women 71.2– while in the US, for men it is 76.2 and for women 81.2. For Mexico, men’s numbers are 72.12 and women’s 77.84. For Japan, the numbers are: 81.25 years for men and 87.32 years for women in 2018. (Numbers from Wikipedia and Google.)
COVID-19 in Mexico: unreported suffering

Mexico has seen 408,449 COVID-19 cases confirmed, with 45,361 deaths– 11% of cases are deaths, according to Worldometer. There are reports that testing is extremely limited by government policy in Mexico. According to Wikipedia, a government agency estimated that there were actually over 2.8 million cases, although their methodology is unknown.
If the death rate were only 1%, which would be low, that would mean that there would be 28,000 deaths. If there were 45,000 deaths, at a death rate of 1%, there would be 4.5 million cases… so your guess about the true figures is as good as mine.
Searching in Google, I was unable to find much recent information about Mexico’s COVID-19 problems. This Vox article from May 13 states that the pandemic in Mexico is being deliberately undercounted.
This article in the Yucatan Times from July 29 details the financial toll that is exacted from patients trying to get treatment for the virus in Mexico. There is, theoretically, public health care there, but the public hospitals are overwhelmed. Private hospitals demand pre-payment of large fees before even accepting patients at all.
This article in the Washington Post from July 2 says that Mexico City’s death rate tripled from March through May. The article includes figures stating 27,394 people died in Mexico City during that period, although the government reported only 4,000 coronavirus deaths. This would suggest that they are reporting less than half of deaths due to coronavirus.
Actually, it is worse than that, because according to the article, it takes at least a year for the government to finish totalling up all deaths for any given period. Add a few thousand more, but at this point, the exact number matters less than the overall picture of devastation.
With the border closed, there is little chance of spillage of Mexican cases into the US. Untold suffering is going on there, and if you think the US has problems, I am sure Mexico’s problems are worse. Our government is not handling the pandemic well, but Mexico’s government is doing very poorly.
I’m not going to look at the numbers from Canada (I’m tired), but all reports are that they are doing far, far better than we are. Fortunately, that border is closed as well.

This editorial published in JAMANETWORK today, July 29, discusses a research article also published today that estimates a roughly 60% reduction in COVID-19 cases and deaths due to school closures in March.
The implications are that re-opening schools will lead to a dramatic increase in cases during an uncontrolled outbreak due to SARS-COV-2. We can’t afford to increase cases, despite the economic and scholastic impact of keeping them closed.
Here are the statistics quoted in the editorial:
Auger et al4 found that school closure was associated with a −62% (95% CI, −71% to −49%) relative change in COVID-19 incidence per week, corresponding to an estimated absolute difference of 423.9 (95% CI, 375.0 to 463.7) cases per 100 000. The authors also reported that school closure was associated with a −58% (95% CI, −68% to −46%) relative change in mortality per week, corresponding to an estimated absolute difference in mortality of 12.6 (95% CI, 11.8 to 13.6) deaths per 100 000. Extrapolating these results to the US population, the authors estimate that school closure may have been associated with 1.37 million fewer cases of COVID-19 over a 26-day period and 40 600 fewer deaths over a 16-day period during the spring of 2020. It is important to emphasize these are estimates.
JAMA. Published online July 29, 2020. doi:10.1001/jama.2020.13092
It is not yet time to re-open schools. I suggest that we wait until January, when it will become clear in what direction this country is heading. Either things will be worse or better. They can’t stay the same.

The reason “He who must not be named” needed to take the screening test for dementia is that His father died of Alzheimer’s Disease (AD.) This disease runs in families to a very large extent (see below for explainer.)
The reason He brags about it is that he misunderstands or chooses to misinterpret the reason he had the test. I think that fundamentally, he misunderstands for two reasons: he wasn’t told the truth about why he was given the test, and/or he doesn’t have the intellectual capacity to make the distinction between dementia and personality disorder.
He doesn’t admit that dementia has nothing to do with his mental “problems”– his problem is what we call personality disorder, meaning there’s something wrong with his personality. What’s wrong? He has sociopathy and malignant narcissism, which are the problems causing the decline of our country.
Not to mention the deep roots of sadism, misogyny, xenophobia, and racism, which go along with his identification with the Republican Party and its nativist wing. I’ll set those things aside today and concentrate on dementia and personality disorder.
Let us not forget Ronald Reagan, who had AD while he was president and died of it. His entire staff knew that he was losing it, but they covered it up because he pushed the right buttons when it came to policy.
What is sociopathy? In basic terms, it’s the lack of a conscience, that thing inside you that makes you do right when other people aren’t looking or don’t stand in your way.
What is malignant narcissism? It is the concentration of your entire being on yourself and the complete absence of interest in anything other than yourself. Other people are only of concern to the extent that they validate you by praising you and doing what you want.
Every subject is of interest only to the extent that it reflects on your glory and your complete mastery. Nothing can be allowed to get in the way.
To a malignant narcissist, anyone who questions or criticizes is automatically an enemy to be destroyed. There is never any sense that one might be wrong or imperfect, or if there is, it must be immediately negated by praise from another or complete destruction of the critic.
To diagnose sociopathy and narcissism, there is the Minnesota Multiphasic Personality Inventory, but He wouldn’t take it– it’s way too long. Instead, one can make these diagnoses on the basis of spontaneous statements and behavior outside of the exam room, as His niece Mary Trump has done.
The “Goldwater Rule” would normally prevent a professional from discussing diagnoses, especially mental, outside of the exam room and without the patient’s consent. There is another doctrine, the “duty to warn” if there is a danger to “self and others.” In this case, anyone who realizes how bad things are has a duty to tell everyone because this patient can be very dangerous.
G-d help this country if this man is re-elected.
Explainer: the causes of dementia, specifically Alzheimer’s Disease.
First, the symptoms: The most common early symptom is difficulty in remembering recent events. As the disease advances, symptoms can include problems with language, disorientation (including easily getting lost), mood swings, loss of motivation, not managing self-care, and behavioural issues.
(references for symptoms: British Medical Journal, 2009 Feb 5;338:b158. doi: 10.1136/bmj.b158. World Health Organization fact sheet.)
Second, the causes: the chance of inheriting (heritability) of AD is estimated between 49% and 79%. This means that AD is caused by problems with your metabolism that you are born with. Your chances of getting AD are less, even if you have metabolic problems, if you exercise (both body and mind) and eat a diet low in animal fat.
Most AD is called “sporadic” because it has not been identified in the patient’s relatives. If He were found to have AD, we would say it was inherited because His father has it.
In sporadic cases as well as inherited ones, the risks are higher with high cholesterol, fatty diet, inactivity, obesity, and lack of mental exercise. Sound familiar? All of these risk factors fit He-who-must-not-be-named.
Luckily for Him, risks are probably less with cholesterol-lowering drugs, which He is taking– but the risk is NOT eliminated just by taking a pill.
A small percentage (roughly 0.1%) of AD is caused by a dominant mutation on regular chromosomes (not X-linked.) These are interesting cases because they are traced to mutations in genes for amyloid precursor proteins (more on these below) or “presenilins” (proteins that sit in the cell membrane and control how calcium crosses into the cells– important in nerves that sit in the hippocampus, a brain region that controls memories.)
In most sporadic cases, like the inherited forms, there is an apolipoprotein called apo-E4 present. It is involved in cases of atherosclerotic heart disease as well as AD. This fat-binding protein is part of fat metabolism in the body and brain, but it may cause heart disease in different ways than it causes brain disease and AD.
In the brain, apolipoprotein E helps to break down amyloid deposits called plaques. When the E4 type malfunctions, especially when body cholesterol levels are high, these deposits can damage nerve cells. Over a lifetime, amyloid plaques that build up eventually kill nerve cells. This has a lot to do with AD, but it’s not the whole story.
Those amyloid precursor proteins mentioned above also play a role. These proteins, when broken down into amyloid beta, accumulate in sheets called amyloid plaques. These are metabolized and removed in the brain by apo-E. Certain types of amyloid beta are harder to break down than others– leading to more and bigger plaques and, eventually, brain damage… thus, AD.
There is actually a known mutation in amyloid precursor protein that protects against AD by reducing breakdown into amyloid beta. The “amyloid precursor proteins” play many physiological roles that are still being evaluated (see the Wikipedia article on these proteins.)
That’s enough science for one post. It all comes from Wikipedia, which is almost 20 years old and getting bigger by the day. I just gave them $5.35 because I was ashamed that they only asked for $1.75 …
This study, from JAMANETWORK on July 17, looked at blood antibody tests done in several large cities in late March of this year. The astounding finding: between 6 and 24 times more patients had antibodies than had been counted by nasopharyngeal swab testing for SARS-COV-2:
In this cross-sectional study of 16 025 residual clinical specimens, estimates of the proportion of persons with detectable SARS-CoV-2 antibodies ranged from 1.0% in the San Francisco Bay area (collected April 23-27) to 6.9% of persons in New York City (collected March 23-April 1). Six to 24 times more infections were estimated per site with seroprevalence than with coronavirus disease 2019 (COVID-19) case report data.
JAMA Intern Med. Published online July 21, 2020. doi:10.1001/jamainternmed.2020.4130
This study has been widely reported recently. Its finding, that an average of ten to twelve times more patients with antibodies were present in each city than had been counted by antigen testing, has not been accounted for.
The conclusion is that many people either had asymptomatic infection or never went to be tested when they had symptoms. This has implications for preventive measures: everyone should be trying to prevent catching this disease all the time, even when they are not around people known to have been infected.
This means that you should be wearing a mask whenever you are around people you don’t know intimately. Even those you know well are potential vectors of disease: every non-household member and even those in your own household.
Previous studies have found ten to twenty percent of household contacts of people with proven COVID-19 become infected within ten days after the virus has been detected. What happens after ten days is unknown.
There have been very few reports of infections among children under ten, but this population has not been well-studied. If schools open next month, we should soon find out how many children have it and how well they pass it on. I would be extremely cautious about contacts with small children.
Children over ten years of age are likely to be just as infectious as adults. This age group includes a large proportion of school children– everyone in fifth grade and above. The vast majority of them will not get sick, even when they are infected, but they will be efficient vectors of disease to their parents, grandparents, schoolteachers, and staff.
The risks of open schools in the USA, with its environment of rapidly expanding infections, are great. For the last week or so, every day has brought over 50,000 new cases, and every day over a thousand people die. The actual number of new cases each day, with a broken testing system, is completely unknown.
Only in a state like Vermont would opening schools for in person attendance be even minimally acceptable.

